
Topic
Complication Signs: What Goes Wrong and What Is Done
Three questions about what goes wrong after filler, what the clinician does in the next hour, and which results can be undone later.
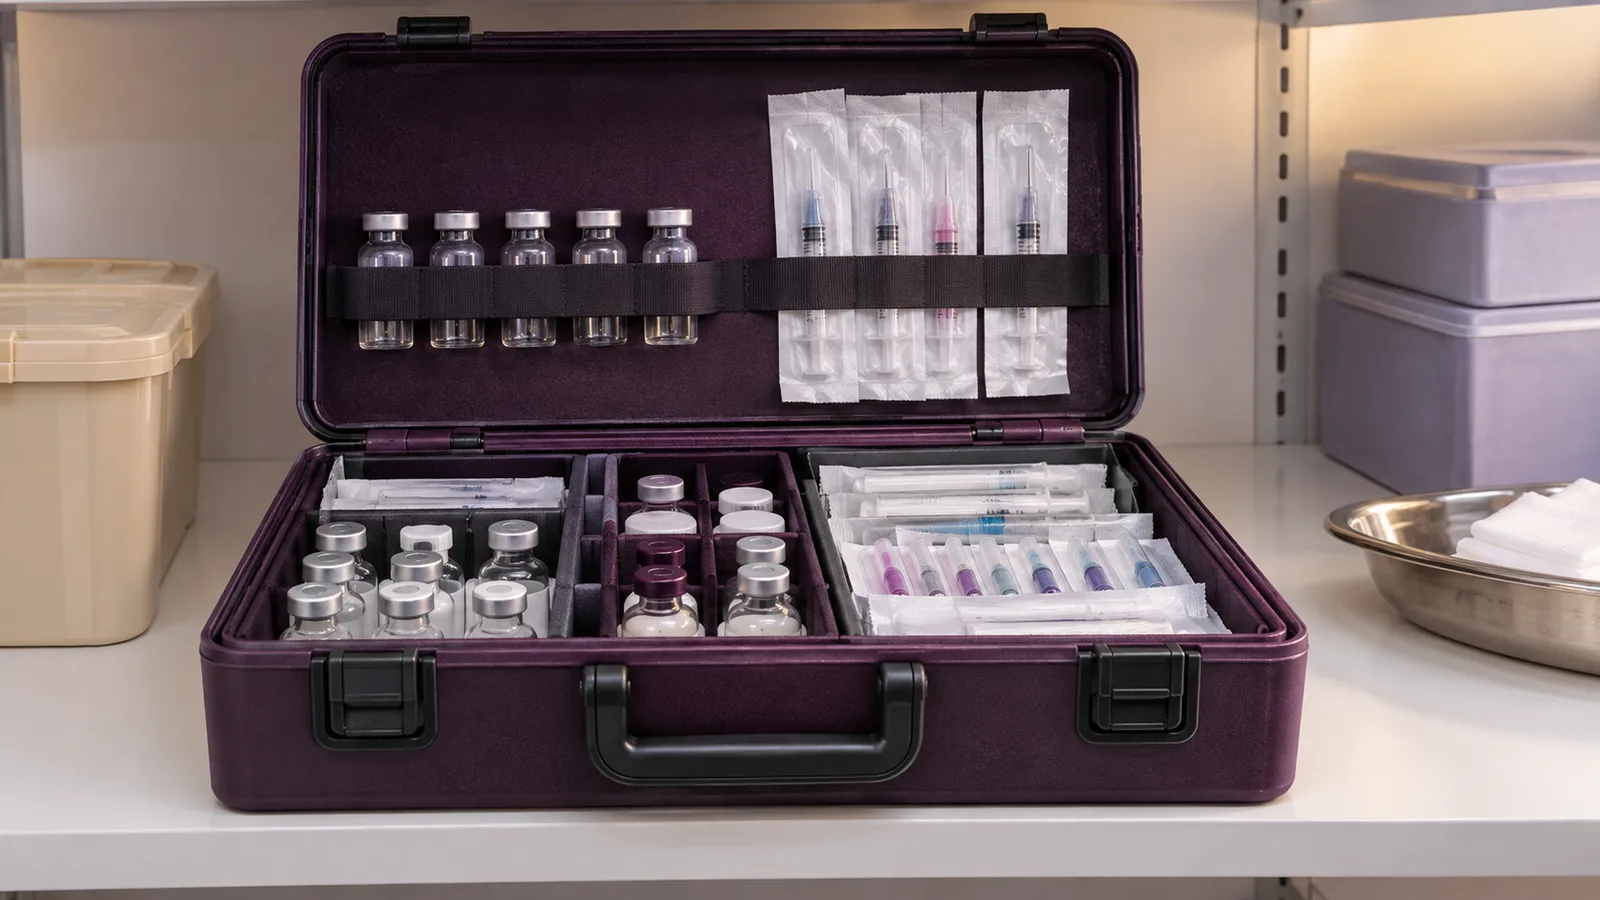
Complications are the part of the consultation most patients remember least, because the consent form covers them in a paragraph and the conversation moves on. They are also the reason the other five topics on this site matter.
Facility standards, injector credentials and supervision are all ways of asking one question: when something goes wrong, who notices, how fast, and what do they do about it.
This topic holds the three questions that come up most often in Hancock Park once a patient starts reading consent forms closely.
What happens when filler enters a vessel, whether dissolving filler harms the surrounding tissue, and whether a result can be undone later if tastes change.
The answers describe what the signs look like, what the clinician's response is, and what a patient can reasonably expect to be told before treatment.
Every page in the topic ends with what to ask before booking, because the answer a clinic gives about complications is the best predictor of how it will handle one.
When the details conflict, start with the vessel question, because it sets the standard for everything else. Vascular occlusion is rare and it is an emergency.
A clinic that injects hyaluronic-acid filler should have hyaluronidase in the room, a written protocol, and a clinician who can say from memory what the first signs look like and how the next hour goes.
A practice that cannot describe that sequence has told the patient what its emergency plan is.
Consent forms are where these answers should already be, and many are not written to be read. A consent form that lists "vascular compromise" with no explanation of what the patient would see or feel is meeting a legal requirement and missing the point.
A good clinic walks through the paragraph out loud.
The third question, reversibility, is where expectations and product choice meet. Hyaluronic-acid fillers can be dissolved. Neurotoxin wears off over months.
Threads are absorbed on their own timetable. Collagen-stimulating fillers, fat transfer and ablative resurfacing cannot be undone, only managed. A patient who wants the option of changing their mind is choosing from a shorter menu, and a clinician should say so before rather than after.
The people asking these questions come from every neighborhood, and the skin tones, budgets and expectations in a waiting room reflect that range. Complication risk is not evenly spread across it.
Deeper skin tones scar and pigment differently after an occlusion or a dissolving reaction, and the consent conversation should account for that rather than assume one face.
Questions in this topic

What happens if filler is placed in a vessel?
Blanching, dusky or mottled skin, pain out of proportion, the time window, and the hyaluronidase protocol that every injecting practice should be able to describe.
Does dissolving filler damage the tissue?
What hyaluronidase acts on, what it leaves alone, and the temporary effects that are sometimes mistaken for damage.

Can results be reversed if preferences change?
Which treatments are reversible, which fade on their own, and which are permanent by design.
About us
How these pages are written
Our editors are independent readers in Hancock Park with no medical license and no clinic to defend. They hold consent forms to the plain-language standard set out in the federal plain-language guidance on Digital.gov.
What a sign means on one face is a question for the licensed clinician who is looking at it.
About us
About these answers
Written from consent forms and the published case literature on filler complications, with the whole city in view: the communities around the Japanese American Cultural & Community Center, the neighborhoods the Los Angeles Neighborhood Land Trust works in.
No one here has a medical license or a clinic to defend. Where a sign or a timeline is described, it is the one the literature describes, and the licensed clinician who has examined the face comes first.



Before booking
Read the vessel question first
It sets the standard for everything else in this topic, because a clinic's answer to it tells a patient what the emergency plan is: what happens if filler is placed in a vessel.